Understanding your ultrasound report
If your scan report mentions a TI-RADS score, it simply describes how suspicious a thyroid nodule looks on ultrasound — on a scale from TR1 to TR5.
On this page
TI-RADS stands for Thyroid Imaging Reporting and Data System. It is a standardised way for a radiologist to describe how suspicious a thyroid nodule looks on ultrasound, using a single score. The version described on this page was published by the American College of Radiology (ACR) in 2017.
The idea is simple. A thyroid lump on its own tells you very little — most are completely harmless. TI-RADS looks at the specific features of the nodule on the scan and turns them into a number, so that two doctors looking at the same nodule describe its risk in a similar way.
The result is a level from TR1 (benign) to TR5 (highly suspicious). The higher the level, the more closely the nodule needs to be looked at — but a high score is still only a flag for further checking, never a diagnosis on its own.
Did you know?
A thyroid nodule is extremely common — the ACR white paper reports that up to 68% of adults have at least one when scanned with high-resolution ultrasound, yet only a small fraction are cancer. TI-RADS exists so that fewer benign nodules are biopsied unnecessarily, while still finding most of the cancers that matter. (Source: American College of Radiology — ACR TI-RADS White Paper.)
Each level reflects how likely a nodule is to be cancerous, based on its appearance on the scan. These are broad, ACR-based risk estimates — your specialist reads them alongside the nodule's size and your own history.
The TI-RADS level on your report
Tap the level on your report to see what it means.
Benign
A TR1 nodule scores 0 points, for example a fluid-filled cyst or a sponge-like (spongiform) nodule. This is a reassuring result, with an estimated cancer risk of no more than 2%. No biopsy needed.
Not suspicious
A TR2 nodule is not suspicious: it looks benign, with an estimated cancer risk of no more than 2%. No biopsy needed. ACR TI-RADS advises no routine follow-up scans, though some doctors still arrange one.
Mildly suspicious
A TR3 nodule is mildly suspicious, with a low estimated risk of cancer, broadly around 5%. Most TR3 nodules are benign and are not usually biopsied straight away.
Moderately suspicious
A TR4 nodule is moderately suspicious, with a higher estimated risk of cancer, broadly 5%–20%. This is the level where a biopsy is often recommended, depending on size.
Highly suspicious
A TR5 nodule is highly suspicious, the highest level, with an estimated risk of cancer of at least 20%. A biopsy is usually advised once the nodule is large enough, so it can be sampled and the answer made clear.
Level not listed
Some reports list the five features without a level. The radiologist adds the points for each feature to reach the level.
No level to check
If your report has no TI-RADS level, the radiologist may have used another scoring system, or none. A specialist can read the report with you, and the consultation is free.
Want a specialist to go through your report with you? The consultation is free.
Book free consultation| Level | What it means | Estimated cancer risk |
|---|---|---|
| TR1 | Benign | No more than 2% |
| TR2 | Not suspicious | No more than 2% |
| TR3 | Mildly suspicious | ~5% |
| TR4 | Moderately suspicious | ~5%–20% |
| TR5 | Highly suspicious | At least 20% |
Whether a nodule is biopsied depends on both its TI-RADS level and its size. ACR TI-RADS sets a size cut-off for each level. Below its cut-off a nodule is not biopsied on its score alone, and follow-up scans are not always advised either.
Even a TR5 nodule is often benign after biopsy. The score sorts nodules by risk — it does not label any of them as cancer.
Risk percentages are broad ACR-based estimates and vary between studies; your specialist interprets them for your specific nodule. Source: American College of Radiology (ACR) TI-RADS. A biopsy decision is never made on the score alone.
Free consultation
A number on a report should never leave you guessing. We walk this journey with you — explaining the score, with no rushed decisions.
Free consultation across our Hyderabad locations. Bring your ultrasound report — we will explain exactly what it means.
This is the single most important thing to understand about your report. TI-RADS estimates risk from the look of a nodule on ultrasound — it cannot see the actual cells. A nodule can look suspicious and be entirely benign, and occasionally a quiet-looking nodule needs a second glance.
The most reliable way to tell whether a nodule is cancer is a fine needle aspiration (FNAC) — a quick, simple test that takes a tiny sample of cells with a very thin needle. TI-RADS does not replace this; it simply helps decide which nodules are worth sampling, so you avoid an unnecessary biopsy of a clearly benign one.
So a higher TI-RADS level is a reason to get a clear answer — not a reason to assume the worst. You can read more about the full pathway on our thyroid cancer diagnosis page.
The radiologist looks at five features of the nodule on ultrasound. Each feature earns points, and the points are added up. The total decides the TI-RADS level — the more suspicious features a nodule has, the higher its score.
These are the ACR TI-RADS points in simple words; the radiologist applies the full chart. For composition, echogenicity, shape and margin, one finding is chosen; for bright spots, every kind seen is added. Every nodule scores 0 points or at least 2, so a total of 1 does not occur.
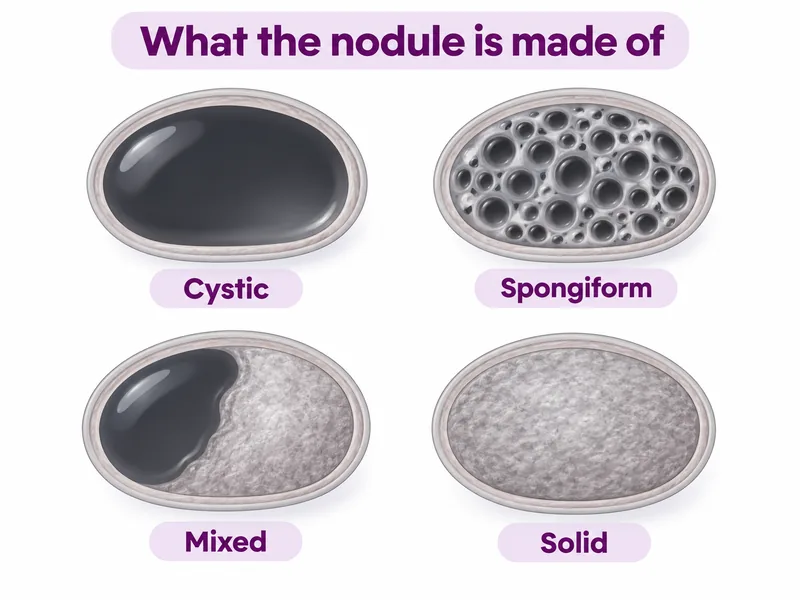
Whether the nodule is solid, fluid-filled (cystic), or a mix of both. A purely fluid-filled nodule is almost always benign and scores no points, while a fully solid one scores more.
ACR points
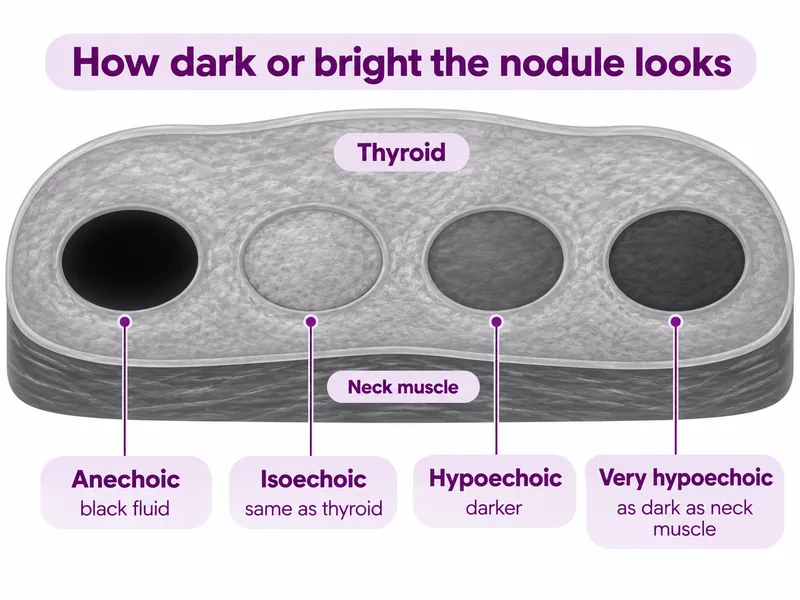
How dark or bright the nodule appears compared with the rest of the thyroid. A nodule that is darker than the nearby neck muscles (very hypoechoic) is more suspicious and scores higher.
ACR points
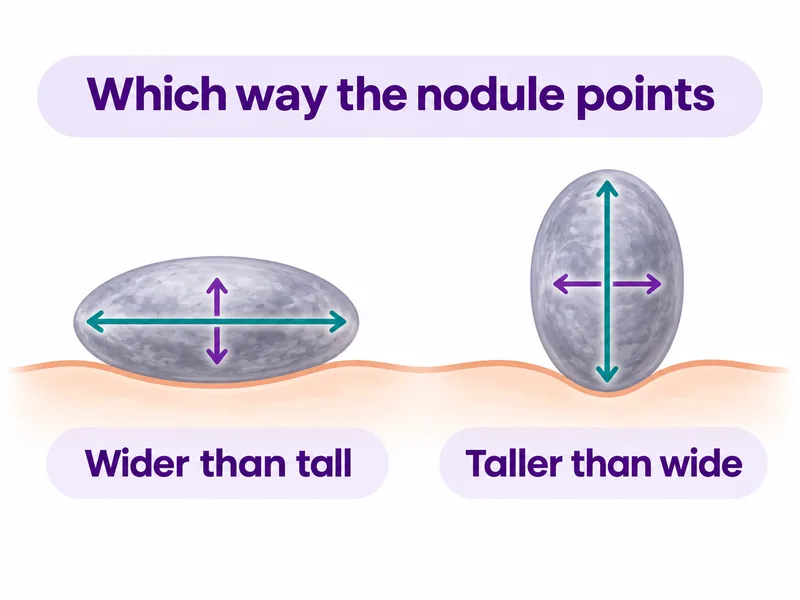
Whether the nodule is "taller-than-wide" — meaning it is deeper than it is broad. This shape is more often linked with cancer, so it adds points.
ACR points
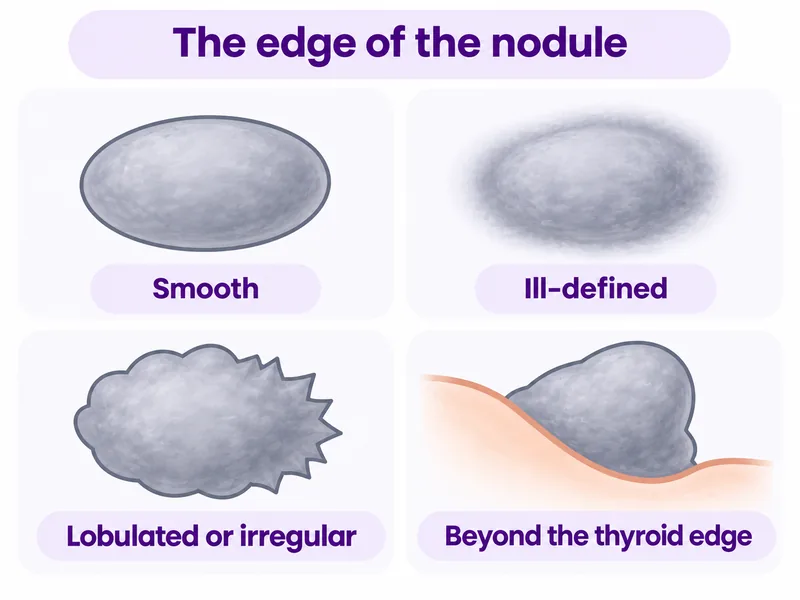
Whether the edge of the nodule is smooth, lobulated, irregular, or pushing beyond the thyroid border. A smooth edge is reassuring; an irregular or extending one scores more.
ACR points
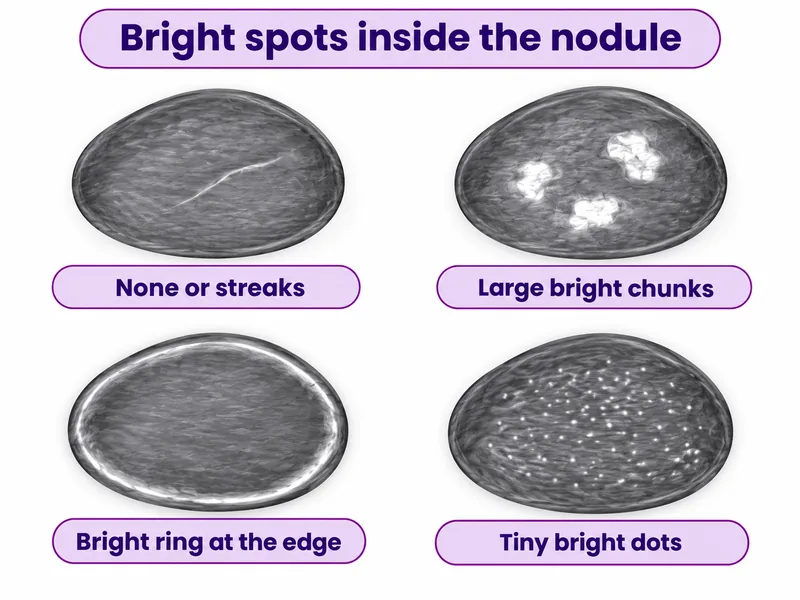
Bright spots inside the nodule, such as microcalcifications. Tiny bright punctate spots are one of the more suspicious signs and score 3 points, the most any one finding earns; different kinds of bright spot are added together.
ACR points
Did you know?
Under ACR TI-RADS, the five features add up to a total: 0 points is TR1, 2 points is TR2, 3 points is TR3, 4–6 points is TR4, and 7 or more points is TR5. The ACR rules are the same in every clinic that uses them and aim for a consistent score, though two radiologists can judge some features differently. (Source: ACR TI-RADS White Paper, JACR.)
Whatever number is on your report, the next step is the same — a calm, clear review by a thyroid specialist, not panic. Here is how to read your result.
TR1 or TR2
Reassuring
No biopsy is needed. ACR TI-RADS advises no routine follow-up scans for these levels, though some doctors still suggest an occasional ultrasound just to confirm the nodule stays stable.
TR3
Low risk
A biopsy is usually advised only if the nodule is large enough; for a smaller one, your doctor decides whether repeat scans are needed.
TR4 or TR5
Worth sampling
A fine needle aspiration is generally recommended once the nodule reaches the size threshold, so you get a clearer answer. This is the most useful time to see a specialist — not because cancer is certain, but because a quick test can remove the uncertainty.
If you are unsure what your score means or whether you need a biopsy, our team is glad to read your report with you.
Learn more about the tests involved on our thyroid cancer diagnosis page, or explore thyroid cancer treatment if a diagnosis has already been made.
If you want your score explained properly, here is what you can expect at CION Cancer Clinics.
Bring an existing ultrasound report and have it reviewed at no cost.
Unhurried time with a specialist to explain your score and what it means for you.
Review close to home, with less travel.
Patients share their experience of CION on Google.
A TI-RADS score is not a verdict — it is a starting point. Book a free consultation and let us turn the number into a plan.
Whether a biopsy is needed depends on both the TI-RADS level and the size of the nodule. Under ACR TI-RADS, a biopsy (FNAC) is generally advised when a TR3 nodule is 2.5 cm or larger, or once a TR4 or TR5 nodule reaches the size cut-off for its level. CION's page on whether a TR4 or TR5 nodule needs a biopsy sets out those cut-offs. TR1 and TR2 nodules are considered benign and do not need a biopsy. Smaller nodules that do not meet the size threshold are not biopsied on the score alone, and whether they are followed with repeat scans depends on their size. Your specialist makes the final call, taking your history into account.
TI-RADS 3 (TR3) means the nodule is mildly suspicious on ultrasound. The estimated risk of cancer is low — broadly in the region of 5%. Most TR3 nodules turn out to be benign. Under ACR TI-RADS, a biopsy is generally advised only if a TR3 nodule is 2.5 cm or larger; a smaller TR3 nodule is not biopsied straight away, and your specialist decides whether it needs follow-up scans. Your specialist will weigh the score against the nodule's size and your own history before recommending the next step.
TI-RADS 4 (TR4) means the nodule is moderately suspicious. The estimated risk of cancer is higher than TR3 — broadly in the region of 5% to 20%. Because of this, ACR TI-RADS generally recommends a fine needle aspiration biopsy (FNAC) for a TR4 nodule once it reaches the size cut-off, and, for a smaller one, your specialist decides whether follow-up scans are needed. A TR4 result does not mean you have cancer; it means the nodule has enough suspicious features to be worth sampling so you get a clear answer.
TI-RADS 5 (TR5) means the nodule is highly suspicious on ultrasound, with an estimated cancer risk of at least 20%. It is the highest TI-RADS level, but it is still not a diagnosis of cancer — many TR5 nodules are biopsied and found to be benign. ACR TI-RADS advises a fine needle aspiration biopsy for a TR5 nodule once it reaches the size cut-off. A TR5 score is the clearest signal that you should see a thyroid specialist so the nodule can be sampled and the situation made clear.
TI-RADS 1 (TR1) means the nodule is benign and scores 0 points, for example a fluid-filled cyst — a reassuring result. TI-RADS 2 (TR2) means the nodule is not suspicious, or benign, with an estimated cancer risk of no more than 2%. Both are reassuring, and neither needs a biopsy under ACR TI-RADS. ACR TI-RADS advises no routine follow-up for TR1 or TR2, though some doctors still arrange an occasional ultrasound, mainly to confirm the nodule stays stable in size. As always, the score is a guide — if anything changes, such as the nodule growing or new symptoms appearing, it is worth getting reviewed again.
A TR4 result means the nodule is moderately suspicious and usually warrants a fine needle aspiration biopsy once it reaches the size cut-off. The sensible next step is to see a thyroid specialist who can review the full ultrasound, confirm whether a biopsy is needed, and arrange it if so. At CION Cancer Clinics you can book a free consultation and bring your report for a free second opinion. A biopsy usually gives a clearer answer, although some samples are inconclusive and need repeating.
The American (ACR) TI-RADS has five levels, TR1 to TR5, and 4a is not one of them. A label like 4a therefore usually comes from a different system. European (EU-TIRADS) and Korean (K-TIRADS) versions also exist, and their levels may not match TR levels. Ask which system your report used. CION's guide to Bethesda biopsy categories explains a separate scale for biopsy samples.
Each nodule can be given its own score. In a gland with many nodules, a report may describe only the most important few. The European guideline asks for at least three, chosen by risk features and size, with suspicious-looking nodules described even when small. CION's guide to how a thyroid nodule is evaluated explains why ultrasound features, not size alone, guide the next step.
Radiologists (doctors who read scans) can judge some ultrasound features differently. Guidelines report moderate to substantial variation between readers. So a small difference in score may not mean the nodule has changed. Take both reports to your treating specialist and ask which features differed. CION's guide to whether thyroid nodules can turn cancerous explains that doctors look for meaningful change in size or features.
TI-RADS systems such as the European one are written for adults. The American Thyroid Association says its adult guideline should not be applied to children under about 18 to 20, who have separate guidelines. That guideline also has separate advice for nodules found in pregnancy, so plans may differ. A specialist can read the report with you, and the consultation is free.
Free consultation
Bring your ultrasound report and a CION specialist will read it with you.
New answers on this page also draw on CION's own published pages on Bethesda thyroid biopsy results, the thyroid ultrasound, how a thyroid nodule is evaluated and whether a benign nodule can turn cancerous.
Medical disclaimer: This content is for informational purposes only and does not constitute medical advice, diagnosis, or treatment. TI-RADS levels, risk estimates and biopsy size thresholds follow the American College of Radiology (ACR) TI-RADS recommendations and may vary with the system in use. ACR TI-RADS is guidance for adults; children and pregnancy need a specialist's own assessment. Always consult a qualified specialist for guidance specific to your situation.
